

Category

Health Conditions & Diseases

Category

A 2026 visual guide to borders, center clearing, scaling, color on different skin tones, nummular eczema, contagiousness, testing, and treatment mistakes

When comparing ringworm vs eczema pictures, the two conditions can look surprisingly similar. Both can cause round, itchy, scaly patches, and the confusion becomes even greater when the eczema is nummular eczema, a type that forms coin-shaped spots.

The most useful visual clue is often the edge of the rash. Ringworm tends to have a more active, raised, scaly outer border with relatively clearer skin toward the center, while eczema is often more uniformly inflamed, dry, cracked, or weepy across the patch.

That rule is helpful, but it is not reliable enough to diagnose every rash from a photo. Ringworm may lose its classic ring shape on certain body sites, eczema can clear in the center as it heals, and steroid cream can change the appearance of a fungal infection. Skin tone also changes how redness appears. On darker skin, both conditions may look brown, gray, purple, or darker than the surrounding skin rather than bright red.

The fastest visual distinction

Ringworm often expands outward with a sharper, raised, scaly edge and partial clearing in the center. Nummular eczema is more likely to look like a solid coin-shaped patch that is dry, crusty, cracked, or weepy throughout. If the picture does not clearly fit either pattern, a clinician can examine the skin and, when needed, test a scraping for fungus.

Key Takeaways

  • Ringworm is a contagious fungal infection. Eczema is inflammatory and not contagious.
  • Ringworm often has a raised, scaly outer border with relative clearing in the center.
  • Nummular eczema is the eczema type most likely to mimic ringworm because its patches are round or oval.
  • Eczema is often itchy and dry, cracked, crusted, blistered, or oozing across the patch.
  • On darker skin, both rashes may look brown, gray, purple, or darker rather than bright red.
  • Ringworm can spread to other people, animals, and body sites. Eczema cannot be caught from someone else.
  • Do not use steroid cream alone on a rash that could be ringworm. Steroids can worsen or disguise fungal infection.
  • A clinician can use a skin scraping or fungal test when the appearance is unclear.

Visual Snapshot: Ringworm vs. Eczema in Pictures

Picture Clue Ringworm Eczema / Nummular Eczema
Shape Often round or ring-shaped and gradually enlarging Round/oval in nummular eczema, or irregular in other eczema types
Outer edge Often raised, scaly, and more active than the center Usually less sharply defined; may be dry, crusted, cracked, or inflamed throughout
Center May look clearer or closer to normal skin May stay inflamed; can also flatten or clear as a patch heals
Scale Often concentrated near the advancing border Can cover much or all of the patch
Moisture Usually dry/scaly on the body May ooze, blister, crust, or become very dry
Number of spots May start as one patch and spread or form overlapping rings May appear as multiple coin-shaped spots, often on limbs
Contagious? Yes No

For medically reviewed examples of the classic fungal patterns, see the American Academy of Dermatology ringworm photo guide.

What Does Ringworm Look Like in a Picture?

Ringworm of the body, called tinea corporis, usually starts as a small scaly patch and slowly expands. The growing edge often looks more inflamed than the middle. That outer rim may be slightly raised, bumpy, or flaky, giving the rash the ring-like appearance that produced the name.

  • A round or oval patch that gradually becomes larger.
  • A raised or wavy border that looks more active than the center.
  • Scale or small bumps concentrated near the edge.
  • Partial clearing in the middle, although this is not always present.
  • One ring or several rings that can overlap.
  • Itching that ranges from mild to intense.

The CDC notes that ringworm on most body skin may have a clear or scaly center, a slightly raised border, and red, red-purple, brown, gray, or black discoloration depending on skin tone. Scalp, groin, foot, beard, palm, and nail infections can look very different and may not form a clean ring.

The CDC ringworm signs and symptoms page includes updated 2026 descriptions for ringworm on the skin, scalp, feet, groin, beard, and nails.

What Does Eczema Look Like in a Picture?

Eczema is a group of inflammatory skin conditions rather than one single rash pattern. Atopic dermatitis, the most common form, often causes very itchy, dry, scaly skin that can become thickened, cracked, raw, blistered, or crusted after scratching.

A typical eczema picture may show patches with softer or less distinct borders than ringworm. The skin may look rough or leathery from repeated rubbing, and the rash may appear in several areas associated with age and body site, such as the face in babies, elbow and knee creases in many children, or hands, neck, eyelids, and flexural areas in adults.

  • Dry, rough, scaly skin around and between patches.
  • Intense itch, often severe enough to disturb sleep.
  • Cracks, scratch marks, or thickened skin from repeated rubbing.
  • Small bumps, blisters, leaking fluid, or crusting during some flares.
  • Patches that return in the same areas over time.
  • Color that may be pink/red on lighter skin or purple, gray, brown, or darker/lighter than surrounding skin on darker tones.

Why Nummular Eczema Looks So Much Like Ringworm

Nummular eczema, also called nummular dermatitis or discoid eczema, is the main reason a search for ringworm vs. eczema pictures can be confusing. It forms round or oval spots that resemble coins, sometimes with enough scaling and center change to imitate a fungal ring.

The American Academy of Dermatology describes nummular eczema as often beginning with tiny bumps or blister-like sores that crust and merge into a raised coin-shaped patch. The patches frequently develop on the legs, forearms, or backs of the hands and can appear on both sides of the body.

Clue More Suggestive of Ringworm More Suggestive of Nummular Eczema
Border Sharper, raised, expanding, scaly rim Less consistently ring-like; may be inflamed across the whole coin
Center Often clearer than the edge May remain dry/scaly, ooze, crust, or later flatten while healing
Skin between patches May look normal Often very dry
Typical sites Anywhere on skin, plus site-specific tinea patterns Often legs, forearms, backs of hands
Trigger pattern Exposure to infected person, pet, surface, or body site Dry skin; may follow a cut, scrape, burn, or insect bite
Spread to others Possible No

For photographs specifically showing coin-shaped eczema, see the AAD nummular eczema signs and symptoms gallery.

How Do the Rashes Look on Darker Skin Tones?

Color words such as red and pink can be misleading when comparing dermatology pictures. In brown and Black skin, inflammation may appear deep brown, gray, violet, purple, or darker than the surrounding skin. Some healing eczema patches can also become temporarily lighter or darker than the person’s baseline skin color.

Ringworm can also be less obviously red on darker skin. The CDC describes patches as potentially red-purple, brown, gray, or black, while the AAD notes that ringworm on skin of color is often brown or gray. This is why shape, scale, border activity, itching pattern, location, and spread are usually more useful than color alone.

Picture-search warning

Online image results often overrepresent lighter skin. A rash does not have to be bright red to be active ringworm or eczema. If the shape seems suspicious but the color looks different from the pictures you found, do not rule either condition out on color alone.

Where on the Body Can Location Help?

Location can provide a clue, but it cannot diagnose the rash by itself. Ringworm changes its appearance depending on the body site, while different types of eczema also favor certain locations.

Body Area Ringworm Pattern Eczema Pattern
Arms / trunk Classic ring-shaped tinea corporis common here Atopic or nummular eczema can also affect these areas
Legs Possible Very common site for nummular eczema
Elbow / knee creases Possible Common pattern in atopic dermatitis
Scalp Scaly patch, broken hairs or hair loss; often needs oral antifungal treatment Dry, itchy or inflamed scalp possible with eczema types
Feet Athlete’s foot: peeling, scaling, cracking, especially between toes or soles Eczema can affect feet but usually does not follow classic athlete’s-foot pattern
Groin Jock itch, often with a scaly advancing edge Contact or atopic dermatitis may occur but is treated differently

Is Ringworm Contagious While Eczema Is Not?

Yes. Ringworm is caused by dermatophyte fungi and can spread through direct skin contact, infected animals, contaminated objects, and shared surfaces. Athlete’s foot, jock itch, scalp ringworm, and many fungal nail infections are related tinea infections caused by the same general group of fungi.

Eczema is not an infection and cannot be caught from another person. A person with eczema can develop a secondary bacterial, viral, or fungal infection on damaged skin, but the underlying eczema itself is not contagious.

How Can a Doctor Tell Ringworm From Eczema?

Many cases can be diagnosed by appearance and history, but circular rashes are one of the situations where testing may be useful. A clinician may gently scrape scale from the active edge of a suspected fungal rash and examine or send the sample for fungal testing. In selected cases, culture, dermoscopy, a swab for infection, or a skin biopsy may be considered.

Testing becomes especially useful when a rash has been treated but is not improving, when it has an unusual appearance, when the scalp or nails are involved, or when a person has already applied a topical steroid that may have changed the fungal rash.

The Treatment Mistake That Can Make the Pictures Harder to Read

A common mistake is applying an over-the-counter steroid cream to any itchy rash. Topical corticosteroids are useful medications for many forms of eczema because they reduce inflammation and itching. They are not antifungal treatment.

The CDC specifically warns against using steroid creams or ointments for ringworm or a rash that may be ringworm. A steroid can suppress redness and scaling without killing the fungus, allowing the infection to spread while looking less typical. This altered appearance is sometimes called tinea incognito.

If you are unsure which rash it is

Avoid treating an undiagnosed circular rash with steroid cream alone. Ringworm usually needs antifungal treatment, while eczema often needs skin-barrier care and anti-inflammatory treatment. Using the wrong treatment can make the rash harder to recognize and delay improvement.

How Is Ringworm Usually Treated?

Ringworm treatment depends on the body site. Limited tinea corporis on ordinary skin is often treated with an antifungal cream, lotion, powder, or ointment. Scalp ringworm usually requires prescription oral antifungal medication because topical creams do not reach infected hair follicles adequately.

Treatment should continue for the recommended duration even if the rash starts looking better sooner. Clothes, towels, bedding, sports gear, and household contact with infected pets may also need attention to reduce reinfection or spread.

How Is Eczema Usually Treated?

Eczema treatment depends on the type and severity. For nummular eczema, dermatologists commonly emphasize restoring the skin barrier with regular fragrance-free cream or ointment moisturizers and avoiding harsh soaps, hot water, and other irritants.

Prescription or clinician-directed anti-inflammatory treatment may include topical corticosteroids or nonsteroid medicines. More extensive or persistent eczema can require additional therapies. If the skin becomes infected, that infection may need separate treatment.

When Should You Stop Comparing Pictures and Get Medical Care?

  • The rash is on the scalp, beard area, nails, around the eyes, or a large body area.
  • There is hair loss, a painful swollen scalp area, pus, or significant crusting.
  • The rash is rapidly spreading or appears after close contact with a known ringworm infection.
  • A circular rash keeps returning or does not improve with appropriate over-the-counter antifungal treatment.
  • You used steroid cream and the rash became larger, less typical, or more widespread.
  • The skin is painful, warm, swollen, draining pus, or covered with yellow/golden crusts.
  • You have fever or feel ill along with the rash.
  • The person with the rash is an infant, is immunocompromised, or has a condition that increases infection risk.

Frequently Asked Questions

What is the easiest way to tell ringworm from eczema in a picture?

Look at the outer border and the center. Ringworm often has a raised, scaly, active edge with relatively clearer skin toward the center. Eczema is more likely to be dry, cracked, crusted, or inflamed throughout the patch. However, nummular eczema can mimic ringworm closely, so this clue is not enough for every case.

Can eczema form a perfect circle?

Yes. Nummular eczema can form round or oval coin-shaped patches and may be mistaken for ringworm. Some patches can also clear in the center as they heal.

Can ringworm look like eczema?

Yes. Ringworm can be dry, itchy, scaly, and inflamed, especially before a clear ring develops. Steroid treatment can also alter the appearance and make the fungal rash resemble eczema or another dermatitis.

Is ringworm always a red circle?

No. It may be pink or red on lighter skin but brown, gray, red-purple, or darker on other skin tones. Ringworm on the feet, scalp, groin, palms, beard, or nails may not look like a classic red ring at all.

Is eczema contagious?

No. Eczema is not contagious. Ringworm is contagious because it is caused by fungi that can spread between people, animals, and contaminated objects or surfaces.

Can I put hydrocortisone on a rash if I am not sure?

It is better not to use steroid cream alone on an undiagnosed rash that could be ringworm. The CDC warns that steroids can make ringworm worse and can change its appearance. If the diagnosis is uncertain, ask a clinician or pharmacist about the safest next step.

How long does ringworm take to appear after exposure?

The CDC says symptoms of ringworm generally appear about 4 to 14 days after skin contact with the fungi that cause the infection.

Can a doctor test for ringworm?

Yes. Depending on the site and appearance, a clinician can take a small skin scraping, hair sample, or nail sample for fungal testing. Testing can be especially helpful when ringworm and eczema look alike.

Bottom Line: Pictures Help, but the Border Is Only a Clue

Ringworm vs. eczema pictures are useful because they teach you where to look: the edge, the center, the scale pattern, the body location, and whether the rash is spreading. A classic ringworm patch grows outward with a more active scaly rim and some center clearing. Classic eczema looks more diffusely dry, itchy, cracked, inflamed, or weepy.

The difficult cases are usually nummular eczema and steroid-altered ringworm. Both can create round patches that break the usual visual rules. That is why a recurring circular rash should not be treated based on internet photos alone, especially when a steroid or antifungal has already been tried without success.

If you are unsure, the most useful next step is not finding a closer-looking photo. It is getting the rash examined and, when appropriate, tested. That matters because ringworm requires antifungal treatment while eczema is treated by calming inflammation and repairing the skin barrier.

Medical note: This article is for general education and cannot diagnose a rash from a description or photograph. It was updated for U.S. readers using information available in August 2026 from the CDC, American Academy of Dermatology, National Eczema Association, and the supplied HealthCentral reference. Seek professional care for uncertain, severe, spreading, infected, scalp, nail, or treatment-resistant rashes.
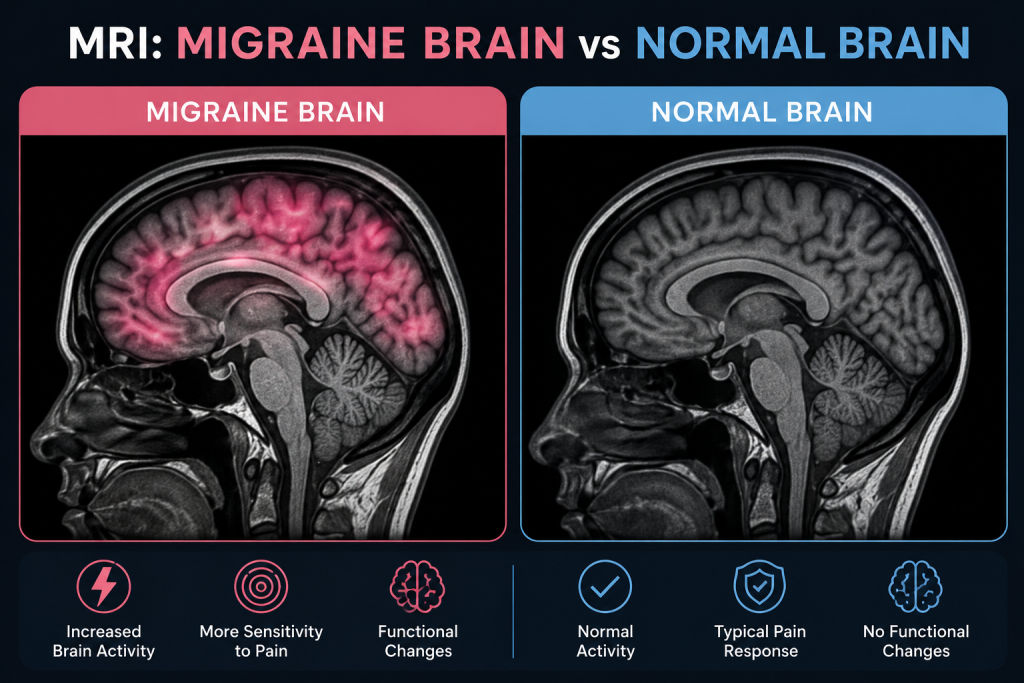

A scan-reading guide to normal MRIs, migraine-associated white-matter spots, and findings that need a different explanation.

A brain MRI can feel like it should provide a simple visual answer to migraine: one scan should look like a migraine brain and another should look normal. In routine medical care, it usually does not work that way.

Migraine is primarily a disorder of brain function and sensory processing. A person can have frequent, disabling migraine attacks and still have a structurally normal MRI. When an MRI does show small bright areas in the white matter, those findings are often nonspecific and can occur in people with migraine, with aging, with vascular risk factors, or in people who have no headache disorder at all.

The practical difference between an MRI migraine brain vs normal brain is therefore not a single signature image. Doctors interpret the scan together with the headache pattern, neurologic examination, age, vascular risks, aura symptoms, and the size, shape, location, and behavior of any MRI findings.

KEY TAKEAWAYS

·        Most people with a typical migraine pattern and a normal neurologic examination do not need brain imaging solely to confirm migraine.

·        A routine structural MRI can be completely normal even when migraine attacks are severe or frequent.

·        Some people with migraine have small white matter hyperintensities, often described as tiny bright spots on T2 or FLAIR images.

·        A 2025 systematic review found that migraine-associated white matter findings are commonly small, supratentorial, and concentrated in deep frontal or parietal white matter, but their clinical significance remains uncertain.

·        White spots do not automatically mean multiple sclerosis, stroke, dementia, or a brain tumor. The MRI pattern and the clinical history determine what they mean.

·        Imaging becomes more important when a headache is sudden, new or changing, occurs with a neurologic deficit, starts after age 50, follows trauma, or appears with other red flags.

Think of the MRI as Three Possible Reports

A useful way to understand migraine imaging is to imagine three common report patterns rather than searching for one “migraine picture.”

MRI Pattern What the Radiologist May See How It Is Usually Interpreted
Report A: Structurally normal MRI No mass, acute stroke, bleeding, hydrocephalus, or significant white matter abnormality Very common in people with migraine; does not argue against a migraine diagnosis
Report B: A few small nonspecific white matter foci Tiny T2/FLAIR bright spots, often in deep or subcortical white matter Can be seen with migraine, aging, or vascular factors; interpreted by pattern and clinical context
Report C: Atypical or concerning pattern Mass effect, acute infarct, unusual enhancement, characteristic demyelinating pattern, or other focal abnormality May point to a diagnosis other than uncomplicated migraine and usually needs targeted follow-up

What Does a Normal Brain MRI Look Like in Someone With Migraine?

On a routine MRI, a “normal” brain means the radiologist does not see a structural abnormality that explains the symptoms. The brain tissue, ventricles, major fluid spaces, and visualized structures have an expected appearance for the person’s age, and there is no acute infarct, suspicious mass, major bleeding, or other significant finding.

That result is entirely compatible with migraine. MRI is excellent at showing anatomy, but a standard clinical scan is not designed to diagnose the moment-to-moment network activity that produces migraine pain, light sensitivity, nausea, aura, and sensory amplification.

Mayo Clinic explains this distinction clearly in its current migraine diagnosis guidance: migraine can involve abnormal brain function while the underlying structural MRI remains normal.

This is why a normal MRI should not be interpreted as “the headache is not real.” It means that the scan did not identify a structural cause for the symptoms.

What Are the White Spots Sometimes Seen on a Migraine MRI?

The most discussed structural MRI finding in migraine is the white matter hyperintensity, often abbreviated WMH. These are bright-appearing areas on certain MRI sequences, especially T2-weighted and FLAIR images.

A 2023 meta-analysis of 30 studies involving 3,502 people with migraine reported a pooled WMH prevalence of 44%. The pooled estimate was 45% in migraine with aura and 38% in migraine without aura. The studies were highly variable, so those percentages should not be used to predict whether one individual will have lesions.

More recent evidence remains cautious. A 2025 systematic review covering approximately 3,600 participants found that white matter findings were frequently reported in migraine, but the clinical meaning, progression, and relationship with migraine features remained uncertain. Across studies, the lesions were most often small, located above the tentorium, and concentrated in deep frontal or parietal white matter.

In other words, these spots can be associated with migraine, but they are not a migraine fingerprint. They are nonspecific imaging findings.

How Can Migraine White-Matter Spots Differ From Other MRI Lesions?

Radiologists do not judge a white spot by brightness alone. They look at its location, shape, number, size, whether it contacts the cortex or ventricles, whether it involves the corpus callosum, brainstem, or cerebellum, whether it restricts diffusion, and whether it enhances after contrast.

Possible Explanation Typical Imaging Clues Why Context Matters
Migraine-associated pattern Often small and punctate; commonly deep or subcortical frontal/parietal white matter Usually nonspecific; clinical context is essential
Age/small-vessel pattern Can involve deep and periventricular white matter; burden often increases with age and vascular risk May prompt review of blood pressure, diabetes, cholesterol, smoking, and vascular health
Multiple sclerosis pattern More likely to include lesions in characteristic periventricular, juxtacortical/cortical, infratentorial, corpus callosal, or spinal-cord locations Diagnosis requires the overall MRI pattern plus clinical and sometimes laboratory evidence
Acute ischemic stroke Often follows a vascular territory or shows restricted diffusion on appropriate sequences Requires urgent clinical correlation
Tumor or mass Usually masslike rather than a few scattered tiny WMHs; may cause swelling, mass effect, or enhancement Needs specialist evaluation based on the exact lesion type

A July 2026 Mayo Clinic guide to white spots on brain MRI emphasizes that white-matter spots may be linked with aging, small-vessel disease, migraine, stroke, multiple sclerosis, and other conditions. Location is useful, but it is only one part of the interpretation.

Does Migraine With Aura Look Different From Migraine Without Aura?

There is no routine MRI finding that reliably separates every person with aura from every person without aura. Population research suggests white matter lesions may be somewhat more common in migraine with aura, but an individual patient with aura can have a completely normal MRI, and a patient without aura can have small nonspecific spots.

Aura itself is a temporary neurologic phenomenon, most often visual but sometimes sensory or language-related. It is thought to involve cortical spreading depolarization, a wave of altered electrical and chemical activity across the cortex. A standard structural MRI is not a live map of that event.

Research MRI techniques such as functional MRI, perfusion imaging, diffusion methods, spectroscopy, or connectivity analysis can identify group-level differences in migraine studies. Those findings are scientifically important, but they are not currently a routine clinical test that lets a radiologist look at one scan and say, “this is definitely migraine.”

Can an MRI Tell Whether Migraine Has Damaged the Brain?

The presence of white matter spots often raises this fear, but the evidence does not support treating every migraine-associated WMH as brain damage from repeated attacks.

The American Migraine Foundation notes that these lesions are generally not linked to neurological impairment or cognitive decline in typical migraine patients. Research continues because migraine, especially migraine with aura, has associations with vascular risk in some populations, but an incidental small WMH is not the same as a clinical stroke.

The 2025 systematic review reached a similarly cautious conclusion: WMHs are common in migraine, yet their prognostic significance is still unclear, and their presence alone does not justify changing routine migraine management in an otherwise typical presentation.

Why Might a Doctor Order an MRI for a Headache?

The purpose of MRI is usually not to prove that migraine exists. It is to investigate features that make a secondary cause more plausible.

The current American College of Radiology Appropriateness Criteria for Headache state that imaging is usually not appropriate for a typical primary migraine or tension-type headache with a normal neurologic examination and no red flags. Imaging becomes appropriate in several higher-risk scenarios.

  • A first or worst headache, especially a sudden thunderclap headache that reaches maximum intensity rapidly.
  • A major change in headache frequency, severity, duration, or clinical pattern.
  • New weakness, numbness, trouble speaking, persistent visual loss, confusion, seizure, or another focal neurologic deficit.
  • New headache beginning after age 50.
  • Headache associated with fever, cancer, significant immunocompromise, or recent head trauma.
  • Features suggesting abnormal intracranial pressure, such as papilledema or certain positional symptoms.
  • New or unusual headache during pregnancy or the postpartum period.
  • Unusual, prolonged, or persistent aura, hemiplegic features, brainstem symptoms, or other atypical migraine presentations.

The exact test may be MRI, CT, vascular imaging, or a combination depending on the suspected problem. A sudden thunderclap headache, for example, is approached differently from a slowly changing chronic migraine pattern.

What Does “Nonspecific White Matter Change” Mean on an MRI Report?

The word nonspecific is important. It means the appearance does not point to one unique diagnosis by itself.

A report might say “a few scattered punctate T2/FLAIR hyperintensities in the subcortical white matter, nonspecific.” In a younger person with a long history of migraine and no neurologic deficit, a neurologist may consider the spots compatible with migraine. In an older adult with hypertension, diabetes, smoking history, or high cholesterol, similar spots may be interpreted in the context of small-vessel disease.

If the lesions have a distribution that is more typical of a demyelinating disease, the radiologist may specifically raise that possibility. The next step can include a neurologic examination, comparison with prior scans, spinal MRI, contrast-enhanced imaging, or laboratory testing. The report wording should be read as a description of probability and pattern, not as a diagnosis by itself.

MRI Migraine Brain vs MS Brain: Why the Difference Is Not Just “White Spots”

Migraine and multiple sclerosis can both be associated with white-matter lesions, which is why incidental spots sometimes cause understandable anxiety. But MS is diagnosed from a combination of clinical history and lesions that demonstrate characteristic distribution and, when applicable, dissemination in space and time.

MS lesions more often involve characteristic areas such as periventricular white matter, the cortex or juxtacortical region, the infratentorial brain, the corpus callosum, or spinal cord. Migraine-associated lesions described in research are more commonly small and deep or subcortical, often in the frontal regions.

There can be overlap, and no online checklist can replace a neuroradiologist or neurologist reviewing the actual images. A few nonspecific spots do not establish MS, and a normal brain MRI in a person with typical migraine is common.

What Questions Should You Ask After a Brain MRI?

If the report contains unfamiliar language, these questions are more useful than searching every word individually:

  • Was the MRI otherwise normal for my age?
  • Are the white-matter spots considered nonspecific, migraine-associated, vascular, or atypical?
  • Does the location or shape suggest multiple sclerosis or another demyelinating condition?
  • Is there evidence of an old or recent stroke?
  • Do I need contrast, vascular imaging, spinal MRI, or another test?
  • Should this MRI be compared with an older scan or repeated later?
  • Do the findings change my migraine treatment or my vascular-risk management?

A stable scan can also be useful. When prior imaging is available, radiologists can determine whether lesions are unchanged or whether there are genuinely new findings.

When Should a Headache Be Treated as an Emergency?

Seek emergency medical evaluation for a sudden severe headache that reaches peak intensity within seconds to minutes, especially if it is new. Also seek urgent care for headache with new weakness, facial droop, trouble speaking, fainting, severe confusion, seizure, new persistent vision loss, a stiff neck with fever, or symptoms after a significant head injury.

People who are pregnant or recently postpartum, are significantly immunocompromised, have active cancer, or develop a major new headache pattern may also need faster evaluation. The urgency comes from the symptoms and clinical setting, not from whether the person has a previous migraine diagnosis.

Frequently Asked Questions

Can a neurologist diagnose migraine from an MRI?

Usually no. Migraine is primarily diagnosed from symptoms, history, and a neurologic examination. MRI is mainly used when clinicians need to rule out another cause or investigate atypical features.

Does a normal MRI mean I do not have migraine?

No. A structurally normal MRI is common in migraine. Migraine can involve abnormal brain function without a visible structural abnormality on routine imaging.

Are white spots common with migraine?

They can be. Studies report variable rates, and a 2023 meta-analysis estimated a pooled prevalence of about 44% among people with migraine. The spots are nonspecific and are not present in everyone with migraine.

Do migraine white spots turn into multiple sclerosis?

Migraine-associated white matter spots do not simply turn into MS. MS is a separate disease diagnosed from its clinical presentation and characteristic imaging and laboratory evidence.

Can MRI distinguish migraine aura from a stroke?

MRI can help evaluate suspected stroke, but the answer depends on timing, MRI sequences, symptoms, and other tests. A first episode of new weakness, speech trouble, or persistent visual loss should be treated urgently rather than assumed to be aura.

Do I need another MRI every year if I have migraine?

Usually not when migraine symptoms are stable, the neurologic examination is normal, and a prior MRI was reassuring. Repeat imaging is driven by new clinical features, concerning findings, or a specific monitoring plan.

Can a brain tumor be mistaken for migraine?

Some tumors can cause headache, but a tumor usually produces a structural abnormality on imaging rather than the tiny nonspecific white-matter spots commonly discussed in migraine. New neurologic deficits or a major change in headache pattern warrant medical evaluation.

The Bottom Line

When comparing an MRI migraine brain vs normal brain, the most important fact is that the two can look exactly the same on a routine structural scan. Migraine is not diagnosed by finding one characteristic lesion.

Some people with migraine have small white matter hyperintensities, often in deep or subcortical frontal and parietal regions. These findings are usually nonspecific, and current research still does not establish that they represent clinically meaningful brain damage in a typical migraine patient.

What matters most is the pattern. A radiologist considers lesion size, location, shape, enhancement, diffusion, age, vascular risk factors, symptoms, and prior scans. If the headache pattern is typical and the neurologic examination is normal, major imaging abnormalities are uncommon. If the symptoms are new, sudden, changing, or neurologically unusual, imaging can become an important part of ruling out a secondary cause.

Medical note: This article provides general educational information and is not a diagnosis. Brain MRI findings must be interpreted by a qualified clinician or radiologist in the context of symptoms, examination, age, health history, and prior imaging. Evidence and imaging guidance were checked against current U.S. sources available in August 2026.

A practical diagnostic pathway for infections, dental causes, salivary gland problems, persistent neck masses, testing, and treatment in 2026.

Finding a lump beneath the jaw can be unsettling. A swollen submandibular lymph node often means the immune system is reacting to a nearby problem, such as a sore throat, cold, skin irritation, or dental infection. The location matters because these nodes drain areas of the mouth, lower face, tongue, gums, and nearby tissues.

Still, not every lump in this area is a lymph node. The submandibular salivary gland sits nearby and can enlarge when a duct is blocked by a stone or when the gland becomes infected. The most useful first step is therefore not guessing the diagnosis, but following the clues: where the lump sits, whether it hurts, how quickly it appeared, what other symptoms are present, and whether it is shrinking or persisting.

KEY TAKEAWAYS

·        Submandibular nodes commonly enlarge because of infections in the teeth, gums, throat, mouth, or nearby skin.

·        A tender, movable node that appears with an obvious infection is usually less concerning than a hard, fixed, painless, or steadily enlarging mass.

·        Adults should not ignore a neck mass that persists without a clear infectious cause, especially when it lasts several weeks or comes with swallowing, voice, mouth, or weight-loss symptoms.

·        Children often develop reactive neck nodes during routine infections, but nodes larger than about 2 centimeters, matted nodes, or persistent unexplained swelling deserve evaluation.

·        Treatment targets the underlying cause. Antibiotics, steroids, or repeated squeezing should not be used as do-it-yourself treatments for an unexplained lump.

First question: Is the lump actually a lymph node?

The term submandibular means “under the lower jaw.” Several structures share this small space, so a lump can come from different tissues. A clinician distinguishes them by location, movement, consistency, and what makes the swelling change.

What it may be Clues that point in that direction
Reactive lymph node Usually a small oval or bean-shaped lump. It may be tender and mobile, especially during a cold, sore throat, dental problem, or skin infection.
Submandibular salivary gland or stone Often feels broader or deeper than a node. Pain or swelling may increase around meals, when saliva production rises.
Dental abscess or jaw infection May occur with toothache, gum swelling, bad taste, facial swelling, fever, or pain when chewing.
Skin cyst Often sits closer to the skin surface and may have a visible pore, redness, or a history of recurring inflammation.
Other neck mass A persistent, firm, fixed, or enlarging lump may require imaging and tissue sampling to identify its origin.

Why do submandibular lymph nodes swell?

Lymph nodes act as immune checkpoints. They filter lymphatic fluid and help immune cells recognize germs or abnormal cells. When tissue in the drainage area becomes inflamed, the nearby nodes may enlarge as immune activity increases. The swelling itself is a sign, not a disease.

The dental and mouth pathway

Teeth and gums are especially important when a node under the jaw becomes tender on one side. Tooth decay, a dental abscess, infected gums, recent dental procedures, mouth ulcers, and infections around a partially erupted wisdom tooth can all trigger nearby nodes. A dental source becomes more likely when there is tooth sensitivity, pain with biting, gum swelling, facial pressure, pus, a foul taste, or reduced ability to open the mouth.

The throat, nose, and skin pathway

Viral upper respiratory infections, strep throat, tonsillitis, influenza, and other infections can cause one or several cervical nodes to react. Cuts, acne, shaving irritation, or infected skin on the lower face may do the same. Direct infection of a lymph node, called lymphadenitis, is more likely when the node is very painful and the overlying skin becomes red, hot, or swollen. Fever may be present, and an abscess can occasionally form.

The bodywide pathway

When lymph nodes are enlarged in several regions, clinicians consider systemic infections and inflammatory conditions. Examples include infectious mononucleosis, cytomegalovirus, HIV, tuberculosis, cat-scratch disease, toxoplasmosis, autoimmune illnesses, and some medication reactions. Travel, animal exposure, recent vaccines, new prescriptions, immune status, and sexual history can all affect the diagnostic plan.

The less common but important pathway

Cancer is not the most common explanation for a submandibular lump, but persistent neck masses require appropriate attention. Lymphoma can begin in lymphatic tissue, while cancers of the mouth, tongue, throat, salivary gland, or other nearby structures may spread to cervical nodes. Risk rises with age and with exposures such as tobacco and heavy alcohol use, but serious causes can occur in people without those risk factors.

A 2025 review in American Family Physician recommends evaluating the location, size, texture, mobility, tenderness, duration, systemic symptoms, exposures, medications, and whether the swelling is localized or generalized. It also notes that persistent lymphadenopathy beyond four weeks or swelling accompanied by systemic symptoms may require laboratory testing and imaging.

What do the feel and timing of the node suggest?

Finding What it may mean
Tender and appeared quickly Often fits an infection or inflammation, particularly when there is a sore throat, tooth problem, fever, or skin irritation.
Soft or rubbery and movable Can occur with reactive nodes. “Movable” is reassuring only when the overall history also looks benign.
Hard, fixed, or matted Needs medical evaluation because these features can occur with malignancy or granulomatous disease.
Painless and steadily enlarging More concerning than a node that becomes tender during a clear infection and then shrinks.
Fluctuant, red, and hot May indicate suppurative lymphadenitis or an abscess that needs prompt treatment.
Present in several body regions Suggests a systemic process rather than a single local dental or throat problem.

Important: Texture and tenderness cannot diagnose the cause on their own. A clinician considers the complete pattern and may use imaging or biopsy when needed.

When should you make an appointment?

Arrange a medical or dental evaluation when the lump has no obvious explanation, is getting larger, or does not begin to settle after the suspected infection improves. The threshold for evaluation should be lower in adults with a new persistent neck mass.

  • The lump remains present for several weeks or keeps returning.
  • It is hard, fixed, matted to nearby tissue, or clearly enlarging.
  • It is larger than expected, especially around 2 centimeters or more in a child.
  • There are drenching night sweats, unexplained fever, persistent fatigue, or unintentional weight loss.
  • You have a mouth sore, tongue lesion, hoarseness, ear pain without an ear infection, difficulty swallowing, or a change in voice that does not resolve.
  • You have ongoing tooth pain, gum swelling, facial swelling, or signs of a dental abscess.
  • Nodes are enlarged in the armpits, groin, or several areas in addition to the neck.

The American Academy of Otolaryngology-Head and Neck Surgery guideline emphasizes prompt, accurate evaluation of adult neck masses when malignancy is possible, rather than allowing repeated empiric treatment to delay diagnosis.

When is swelling under the jaw urgent?

Seek urgent care the same day for rapidly worsening pain, high fever, spreading redness, pus, significant facial swelling, dehydration, or an inability to open the mouth normally. Go to an emergency department for trouble breathing, drooling with inability to swallow, severe neck stiffness, swelling that pushes the tongue upward, confusion, fainting, or other signs of a deep neck infection or airway problem.

What happens during the medical evaluation?

The workup usually follows a sequence rather than jumping immediately to biopsy. The purpose is to identify an obvious local cause while recognizing features that require faster investigation.

  1. History: The clinician asks when the lump appeared, whether it is changing, recent illnesses, dental symptoms, pain with meals, travel, animal contact, medication changes, vaccines, immune conditions, tobacco or alcohol exposure, and symptoms such as fever, night sweats, or weight loss.
  2. Focused examination: The mouth, teeth, gums, tongue, tonsils, skin, salivary glands, ears, and neck are examined. The clinician checks node size, tenderness, texture, mobility, and whether other lymph node regions are involved.
  3. Targeted tests: A complete blood count, inflammatory markers, throat testing, viral testing, tuberculosis testing, or other labs may be chosen based on the history. Not everyone needs the same panel.
  4. Imaging: Ultrasound is commonly the first imaging test for peripheral lymphadenopathy in children age 14 and younger. Adults with persistent or higher-risk neck lymphadenopathy may need contrast-enhanced CT or MRI.
  5. Tissue sampling: Fine-needle aspiration, core needle biopsy, or excisional biopsy may be used when imaging is suspicious, the cause remains unclear, or the node does not resolve as expected. Core biopsy can provide more tissue architecture than a simple aspiration.

The Merck Manual overview of lymphadenopathy notes that many people with newly identified localized nodes and no red flags can be observed for up to about four weeks, while persistent unexplained nodes, generalized swelling, or concerning features call for further testing. Observation is a clinical decision, not a reason to ignore changes.

How is a swollen submandibular lymph node treated?

There is no medication that treats “a swollen node” as a stand-alone diagnosis. Treatment is directed at the cause.

When the cause is viral

Supportive care may be enough for an uncomplicated viral illness. Rest, appropriate fluids, and over-the-counter pain or fever medication may help when safe for the individual. The node can remain noticeable for a while after the infection improves because immune tissue may shrink gradually.

When the cause is bacterial

Antibiotics are used when a clinician identifies or strongly suspects a bacterial infection, such as bacterial lymphadenitis, strep throat, or a dental infection. An abscess may require drainage. Antibiotics do not treat viral illness, lymphoma, salivary stones, or other nonbacterial causes, so taking leftover medication can delay the correct diagnosis.

When the cause is dental

Dental treatment may involve drainage, root canal therapy, extraction, periodontal care, or antibiotics when the infection has spread or systemic symptoms are present. Pain relief alone does not remove the source of an abscess. Facial swelling, fever, or difficulty swallowing requires prompt attention.

When the cause is a salivary stone

Management may include hydration, warm compresses, gentle gland massage, and measures that stimulate saliva, but only after a clinician confirms the likely problem and checks for infection. Recurrent obstruction, severe pain, or infection may require an ear, nose, and throat specialist or oral surgeon.

When the cause is inflammatory or malignant

Autoimmune disease, granulomatous disease, lymphoma, leukemia, and metastatic cancer require condition-specific treatment. Corticosteroids should generally not be started for unexplained lymphadenopathy before diagnosis because they can temporarily shrink lymphoma-related nodes and interfere with tissue interpretation.

What should you avoid doing at home?

  • Do not repeatedly squeeze, dig at, or aggressively massage an unidentified lump.
  • Do not start leftover antibiotics or someone else’s prescription.
  • Do not take corticosteroids simply to make the node shrink before the cause is known.
  • Do not assume that a painless lump is harmless because it does not hurt.
  • Do not rely on size alone. Trend, texture, duration, symptoms, age, and location all matter.

How long can a reactive node stay enlarged?

A node caused by a routine infection may start to soften and shrink as the illness resolves, but it can remain palpable after other symptoms disappear. What matters is the direction of change. A node that is steadily getting smaller is different from one that is unchanged, enlarging, recurring, or becoming firmer. Persistent swelling beyond roughly four weeks, especially without a clear cause or with systemic symptoms, generally warrants reassessment.

Does age change the level of concern?

Yes. Children frequently develop reactive cervical nodes because their immune systems encounter many respiratory and throat infections. Ultrasound is often favored first when imaging is needed. Even so, a very large node, hard or matted nodes, prolonged unexplained swelling, supraclavicular nodes, or systemic symptoms should not be dismissed.

In adults, a persistent neck mass deserves more deliberate evaluation because the probability of malignancy increases with age. A new lump that lasts, enlarges, or appears without an obvious infection should be assessed rather than repeatedly treated as “swollen glands.”

Questions worth bringing to the appointment

  • Does this feel like a lymph node, salivary gland, cyst, or another type of mass?
  • Is there evidence of a dental, throat, skin, or salivary infection?
  • What change should I expect, and by what date should it be smaller?
  • Which symptoms would mean I need urgent care?
  • Do I need ultrasound, CT, MRI, blood tests, dental imaging, or a biopsy?
  • Should I see a dentist, primary care clinician, pediatrician, ENT specialist, hematologist, or oral surgeon?

The practical bottom line

Most swelling in a submandibular lymph node is reactive and linked to a nearby infection, particularly in the mouth, teeth, throat, or skin. Tenderness, mobility, a clear infectious trigger, and gradual improvement are generally reassuring features. They do not replace evaluation when the pattern is unusual.

A hard, fixed, painless, steadily enlarging, or persistent lump should be examined, as should swelling associated with night sweats, unexplained weight loss, mouth or throat symptoms, widespread nodes, or significant dental or facial infection. The right next step may be simple observation, dental care, laboratory testing, imaging, or tissue sampling. The goal is not to fear every lump, but to avoid overlooking one that is behaving differently from a routine reactive node.

Medical note: This article is for general educational purposes and does not diagnose a neck lump or replace care from a licensed healthcare professional. Seek urgent help for breathing or swallowing difficulty, rapidly spreading swelling, or severe illness.

An evidence-based look at the thyroid condition she discussed publicly, the symptoms that can be missed, and the limits of diagnosing anyone through headlines or appearance.

The phrase Wendy Williams Graves disease became widely searched after the television host told viewers in 2018 that she was living with Graves’ disease and hyperthyroidism. Her disclosure brought unusual public attention to an autoimmune thyroid disorder that can affect heart rate, sleep, mood, weight, muscles, eyes, and day-to-day stamina.

Her story is useful as an awareness starting point, but it is not a medical chart. Public appearances cannot show whether Graves’ disease is active, in remission, controlled by medication, or connected to any later health development. The safest way to understand the condition is to separate verified public statements from general medical facts.

Key Takeaways

Wendy Williams publicly disclosed Graves’ disease and hyperthyroidism in 2018. Graves’ disease is an autoimmune cause of an overactive thyroid, not simply a “fast metabolism.” Symptoms can affect many body systems and may be mistaken for stress, menopause, anxiety, or overwork. Treatment may involve antithyroid medication, radioactive iodine, surgery, and symptom control. Eye disease can follow a different course from thyroid hormone levels. Her current thyroid status is private and cannot be determined from media coverage.

The Public Moment That Changed the Conversation

On February 21, 2018, Williams announced on her daytime program that she had Graves’ disease and hyperthyroidism and would take a medically recommended break. Contemporary reporting noted that her team said she had been dealing with Graves’ disease for years. ABC News documented that announcement, including her description of thyroid-related eye changes and the need to get her medication and hormone levels back in balance.

That disclosure mattered because Graves’ disease often looks nonspecific from the outside. A person may be exhausted but unable to sleep, lose weight while eating normally, feel overheated, experience a racing heartbeat, or become unusually irritable. Those changes can be explained away as work stress or aging until blood tests reveal an overactive thyroid.

What Is Publicly Known, and What Is Not?

Supported by public reporting Not possible to conclude from public reporting
Williams said she had Graves’ disease and hyperthyroidism. Whether her Graves’ disease is currently active, controlled, or in remission.
She publicly connected eye changes and a need for medical leave with her thyroid condition. Whether any later symptom, diagnosis, or career event was caused by Graves’ disease.
She has also separately discussed lymphedema. That lymphedema and Graves’ disease are the same condition or have the same cause.

Graves’ Disease Is an Immune Signal Problem

The thyroid is a small gland at the front of the neck, but its hormones influence nearly every organ. In Graves’ disease, the immune system produces antibodies that act like a stuck accelerator. These antibodies stimulate the thyroid to release more hormone than the body needs. The result is hyperthyroidism, a state in which many body processes run too fast.

The National Institute of Diabetes and Digestive and Kidney Diseases estimates that Graves’ disease affects nearly 1 in 100 Americans and causes about 4 out of 5 cases of hyperthyroidism in the United States. It is more common in women and in people older than 30, although it can occur at other ages.

The “Signal Map”: How an Overactive Thyroid Can Show Up

Body system Possible signs Why it may be overlooked
Heart and circulation Fast pulse, pounding heartbeat, irregular rhythm, higher blood pressure May be blamed on caffeine, panic, or poor conditioning
Nervous system Tremor, nervousness, restlessness, irritability, trouble sleeping May resemble anxiety or chronic stress
Metabolism Weight loss, heat intolerance, sweating, increased appetite Weight change may be welcomed instead of investigated
Muscles and bones Weakness, fatigue, reduced exercise tolerance, bone loss over time Fatigue may be blamed on age or a busy schedule
Digestive and reproductive systems Frequent bowel movements, menstrual changes, fertility concerns Symptoms may be treated separately
Eyes Dryness, grittiness, swelling, light sensitivity, bulging, double vision Eye symptoms may be mistaken for allergies or lack of sleep

Why Did Her Eyes Become Part of the Discussion?

Graves’ disease can affect tissue around the eyes, producing thyroid eye disease, also called Graves’ ophthalmopathy. This is not simply a cosmetic change. Inflammation can cause dry or gritty eyes, eyelid swelling, pressure, light sensitivity, bulging, pain with eye movement, or double vision. Rarely, severe swelling can threaten vision.

The eye condition and the thyroid condition are related, but they do not always move together. Eye symptoms can begin before hyperthyroidism is diagnosed, appear during treatment, or continue after thyroid hormone levels normalize. Smoking and nicotine exposure are especially important because they increase the risk and severity of thyroid eye disease.

Urgent eye warning

New loss of color vision, reduced vision, severe eye pain, inability to close the eyelids, or rapidly worsening double vision deserves prompt medical assessment. These are not symptoms to monitor through photographs or social media commentary.

How Doctors Confirm Graves’ Disease

A clinician does not diagnose Graves’ disease from weight, behavior, eye appearance, or a single symptom. The evaluation usually combines a medical history, a neck and eye examination, pulse and blood pressure checks, and laboratory testing.

  • TSH is usually low when the thyroid is producing too much hormone.
  • Free T4 and sometimes T3 help show the degree of thyroid hormone excess.
  • Thyroid-stimulating immunoglobulin or TSH receptor antibody testing can support a Graves’ disease diagnosis.
  • A radioactive iodine uptake test or thyroid scan may show diffuse overactivity throughout the gland.
  • Doppler ultrasound may be used when radioactive iodine testing is not appropriate, including in pregnancy or breastfeeding.

Testing also helps separate Graves’ disease from thyroiditis, toxic thyroid nodules, medication effects, and other causes of hyperthyroidism. That distinction matters because the treatments are not interchangeable.

Treatment Has Three Different Jobs

1. Calm the immediate symptoms

Beta-blockers may be prescribed to reduce a racing heart, tremor, and nervousness while thyroid-specific treatment begins to work. They do not stop the thyroid from producing excess hormone, but they can make a patient feel better relatively quickly.

2. Reduce or remove excess thyroid hormone production

The main treatment routes are antithyroid medication, radioactive iodine, and thyroid surgery. The American Thyroid Association’s Graves’ disease guidance explains that methimazole is commonly used, while propylthiouracil is reserved for certain situations. Radioactive iodine gradually destroys overactive thyroid cells. Thyroidectomy removes most or all of the gland and is often considered when a large goiter, suspicious nodule, medication problem, pregnancy-related issue, or severe eye disease changes the risk-benefit calculation.

Radioactive iodine and surgery frequently lead to hypothyroidism. That outcome is expected and treated with daily thyroid hormone replacement. It does not mean treatment failed.

3. Protect the organs affected by the disease

Treatment may also address thyroid eye disease, bone health, heart rhythm, pregnancy planning, or severe muscle weakness. Eye care can range from lubricating drops and smoking cessation to immune-directed medication, radiation in selected cases, or surgery. Management should be coordinated with an endocrinologist and, when needed, an ophthalmologist who has experience with thyroid eye disease.

Why Medical Leave Can Help, but Rest Is Not the Cure

Williams’ temporary leave highlighted an important reality: uncontrolled hyperthyroidism can make normal work demands difficult. Rest can reduce strain while medication is adjusted, sleep improves, and heart rate comes under control. Still, Graves’ disease is not cured by taking time off. The immune-driven thyroid overactivity requires medical monitoring and, in many cases, long-term treatment.

Patients also need repeat blood tests because symptoms may improve before hormone levels fully normalize, or laboratory values may change before the person notices a difference. Medication doses that are too high can shift someone into hypothyroidism, which has its own symptoms and risks.

Graves’ Disease and Lymphedema Should Not Be Blended Together

Williams has publicly discussed both Graves’ disease and lymphedema. They are separate medical conditions. Graves’ disease is an autoimmune thyroid disorder. Lymphedema is swelling caused by impaired movement of lymph fluid. A rare Graves-related skin condition called pretibial myxedema can cause thickened, reddish skin on the shins or feet, but it is not a general explanation for every form of leg or ankle swelling.

This distinction matters for readers searching celebrity health stories. Similar-looking symptoms do not prove a shared cause, and one diagnosis should not be used to reinterpret every later symptom.

Can Graves’ Disease Go Away?

Some people enter remission after a course of antithyroid medication, meaning thyroid function remains normal after the drug is stopped. Others relapse months or years later. Factors such as antibody levels, thyroid size, smoking, disease severity, and treatment history can influence the likelihood of remission, but no public image or interview can reveal an individual patient’s status.

After radioactive iodine or complete thyroid removal, the thyroid can no longer overproduce hormone in the same way, but lifelong thyroid hormone replacement is usually needed. Thyroid eye disease may still require separate follow-up because it can remain active even when thyroid blood tests are controlled.

Five Lessons From Wendy Williams’ Disclosure

A busy life can hide a medical problem. Insomnia, irritability, sweating, fatigue, and weight change may be rationalized until several symptoms form a pattern.

Eye changes deserve medical attention. Dryness, swelling, bulging, or double vision can be part of thyroid eye disease and should not be dismissed as appearance alone.

“Hyperthyroidism” and “Graves’ disease” are related, but not identical terms. Hyperthyroidism describes excess thyroid hormone. Graves’ disease is one autoimmune cause of it.

Visible improvement does not prove remission. Only clinical follow-up and laboratory testing can show whether thyroid activity is controlled.

Celebrity disclosure can raise awareness, but it cannot replace individual care. Readers should use the story as a prompt to recognize symptoms, not as a template for self-diagnosis.

When Should Someone Ask for a Thyroid Evaluation?

A primary care clinician or endocrinologist may consider thyroid testing when several symptoms occur together, especially a fast or irregular heartbeat, unexplained weight loss, heat intolerance, tremor, neck swelling, persistent insomnia, unusual weakness, or new eye symptoms. People with a family history of autoimmune thyroid disease or another autoimmune condition may have a higher index of suspicion.

Emergency symptoms

Call 911 for chest pain, fainting, severe shortness of breath, a very rapid or irregular heartbeat with weakness, new confusion, high fever, or severe agitation. Rarely, uncontrolled hyperthyroidism can escalate into thyroid storm, a life-threatening emergency.

Questions Readers Commonly Ask

Did Graves’ disease cause all of Wendy Williams’ later health problems?

That cannot be concluded from public information. She has discussed more than one health condition, and only her treating clinicians can determine whether any conditions are related.

Is Graves’ disease caused by stress?

Stress may affect symptoms or act as a trigger in a susceptible person, but Graves’ disease is an autoimmune disorder influenced by multiple genetic and environmental factors. Stress alone is not a complete explanation.

Can Graves’ disease change personality or mood?

Excess thyroid hormone can contribute to irritability, anxiety, restlessness, poor sleep, and difficulty concentrating. These symptoms should be evaluated medically rather than assumed to be a personality change.

Does everyone with Graves’ disease develop bulging eyes?

No. Many people never develop clinically significant thyroid eye disease. Others have mild dryness or swelling, while a smaller group develops more visible or serious symptoms.

Should people with Graves’ disease avoid iodine?

Large iodine exposures, including some supplements and seaweed products, can worsen hyperthyroidism in susceptible people. Patients should discuss supplements, multivitamins, contrast imaging, and dietary changes with their clinician rather than adopting a restrictive diet on their own.

The Bottom Line

Wendy Williams helped bring Graves’ disease into mainstream conversation by speaking publicly about her diagnosis, eye symptoms, and need for medical leave. The larger lesson is not to diagnose her current health from a distance. It is to recognize that an autoimmune thyroid disorder can create widespread symptoms, that eye disease may require separate care, and that effective treatment depends on laboratory monitoring and an individualized plan.

Anyone who recognizes a cluster of symptoms should seek a proper thyroid evaluation rather than relying on a celebrity comparison. Graves’ disease is treatable, but untreated hyperthyroidism can affect the heart, bones, muscles, fertility, pregnancy, and vision.

Authoritative external resources

ABC News: Wendy Williams’ 2018 public disclosure. National Institute of Diabetes and Digestive and Kidney Diseases: Graves’ disease symptoms, diagnosis, and treatment. American Thyroid Association: patient guidance on Graves’ disease and treatment options.

Medical disclaimer: This article is for general educational purposes. It does not diagnose Wendy Williams or any reader, and it does not replace care from a qualified healthcare professional.
